At New England Center for Pelvic Health, we take a minimally invasive approach to surgery whenever possible. Using Laparoscopic techniques causes less pain, less bleeding, and less risk of infection. In most cases, patients are treated in outpatient surgeries and are back to routine activities within a very short time.
Our approach is designed to reduce the likelihood of recurring surgeries. Carefully listening to each patient’s history, we gain valuable information regarding the source and location of the pain, and this assists and guides Dr. Lucas at the time of surgery.
Our patients enjoy the personal attention of a small practice with the expertise and knowledge of a sophisticated specialty clinic.
This outpatient procedure involves looking into the uterine cavity with a tube with a fiber-optic light. Since there is no incision, there is hardly any discomfort, and regular activities can be resumed immediately. When appropriate, a diagnostic hysteroscopy can be combined with a minimally invasive D&C or an endometrial biopsy in the office, reducing the need for multiple procedures. A traditional “blind” Dilatation and Curettage, “D&C”, may miss up to 60% of the surface area of the uterine cavity. Hysteroscopy allows visualization of the entire uterine cavity. This procedure allows the surgeon to diagnose and treat abnormal uterine bleeding. Normalizing the uterine cavity will also help the chance of conceiving.

This outpatient procedure involves looking directly into the bladder cavity and urethra using a thin tube equipped with a fiber-optic light and camera. Because there is no incision, discomfort is minimal and normal activities can typically be resumed quickly. Beyond standard visual diagnosis of chronic urinary symptoms or bladder pain, cystoscopy allows us to perform therapeutic procedures during the same visit—including bladder hydrodistention (gently expanding the bladder under controlled pressure to evaluate capacity and relieve pain from interstitial cystitis) and bladder instillation procedures (delivering soothing, targeted medications directly into the bladder to calm inflamed tissue and reduce pelvic discomfort).

This outpatient procedure involves hysteroscopic removal of uterine fibroids from the uterine cavity. Control of bleeding is excellent, fertility is good, and when the patient conceives she will deliver vaginally since there is no incision in the outer uterine wall.

At our clinic, we understand that certain routine gynecological procedures can be a source of anxiety and discomfort. That’s why we offer nitrous oxide sedation using Nitronox™, a safe and effective solution to manage pain and relieve anxiety during procedures like IUD placement, colposcopy, injections, and endometrial biopsy.

There are four options for treating endometriosis with laparoscopic surgery which include:
1) laser vaporization
2) electrical cautery/fulguration
3) ultrasonic coagulation, or the most effective
4) laparoscopically excising the endometriosis by means of going around, underneath, and completely removing the endometriosis and fibrosis entirely.
This last option, laparoscopic excision of endometriosis, is Dr. Lucas’ approach. As head surgeon of the New England Center for Endometriosis, Dr. Lucas is dedicated to the safe and thorough removal of endometriosis lesions throughout the abdomen.
Endometriosis starts out superficial in the lining of the body cavity. Over time, with menstrual cycling of estrogen, it will invade progressively deeper into the tissues. When endometriosis invades deeper than superficial application of laser or electrical energy penetrate, these modalities may not be sufficient to treat these deep lesions. There is also some concerns that the burning may leave more tissue damage that now just overlies the endometriosis that was unable to be treated. These may cause recurring pain for the patient, resulting in surgery after surgery. Almost all centers that specialize in endometriosis, in and out of the USA, perform laparoscopic excisional surgery for endometriosis.
As endometriosis invades progressively deeper into the tissues, the endometriotic lesions will bleed into themselves, creating a blood-filled cyst, or endometrioma (“endometri” refers to endometriosis, and “oma” means new growth). Ovarian endometriomas do not occur as isolated findings, and there is usually endometriosis involving the pelvic sidewalls and ligaments that needs to be excised. It is necessary for the surgeon to excise the cyst wall from the ovary, and repair the ovary, to have the best chance of saving the ovary and avoiding recurrence of the endometrioma.
The most common surgical finding of endometriosis is fibrosis and scarring (“adhesions”) it leaves behind. If adhesions are felt to be due to previous surgery, then the adhesions can be just divided. If adhesions are felt to be related to endometriosis, then it is necessary for the surgeon to come around both sides of adhesions and remove the scarring/adhesions.
If you’re ready to get started, or if you have any questions, please call us or send us a message, we’d love to hear from you.
Our Endometriosis center focuses on thorough excision of Endometriosis and associated fibrosis, with the restoration of normal anatomy. We do everything possible to help each patient get long-term pain relief and minimize repeat surgeries. While our focus is on the excision of endometriosis for pain relief, many go on to have successful pregnancies.
This outpatient procedure involves laparoscopic removal of uterine fibroids (muscle tumors in the uterine wall) with repair of the uterine wall. This outpatient approach is associated with less pain, fewer adhesions, and a quicker recovery than the open approach. The uterus is repaired with the same size sutures and strong closure as when done open. Other conditions such as endometriosis and adhesions can be treated at the same time.
Uterine fibroids can be deep within the uterine wall, known as Intramural (“mura” means wall) or so large that they go from inside the uterine cavity, through the uterine wall, to the outside of the uterus, known as Trans-mural. Uterine fibroids can be mostly on the outside of the uterus, known as Subserosal.

This outpatient procedure involves laparoscopic removal of the cervix and uterus, with or without removal of the ovaries. Fallopian tubes are often removed since it is now believed that fallopian tubes are the source for certain types of ovarian cancer. This outpatient approach is associated with less pain, less bleeding, less infection, fewer adhesions, and a quicker recovery than the open approach. Other conditions, such as endometriosis and adhesions, can be treated at the same time. Some pelvic support procedures can be performed at the same time. This procedure is performed by laparoscopy with 3 small (8mm) abdominal incisions. There is also a healing incision inside the vagina where the vaginal apex is closed (Where the cervix/uterus was connected).

About 600,000 hysterectomies are performed annually in the U.S., making it the second most common major surgery.
This outpatient, laparoscopic procedure removes the uterus while preserving the cervix, with the option to keep or remove the ovaries. Fallopian tubes are often removed due to cancer risk. Compared to open surgery, it offers less pain, bleeding, and recovery time, and can also address conditions like fibroids, endometriosis, and adhesions.
Total Hysterectomy (“hyster” means uterus, “ectomy” means to remove) is the removal of the uterine body and cervix.
Ovaries and fallopian tubes can be removed or kept in place.
Partial, Subtotal, Supracervical Hysterectomy is removal of the uterine body and the patient keeps the cervix.
Ovaries and fallopian tubes can be removed or kept in place.
Advantages:
Some patients believe this procedure may help maintain sexual function. In reality, sexual outcomes after a hysterectomy depend more on the reason for the surgery—if a painful or limiting condition is treated, sexual activity often improves.
Advantages of a supracervical hysterectomy:
Disadvantages:
Bleeding or pain from the cervix can still happen after a supracervical hysterectomy. If part of the cervical canal remains, some bleeding may continue. If most of it is removed, bleeding is usually minimal or stops.
Patients who choose this procedure should understand:
The best surgical option depends on each patient’s needs and priorities.
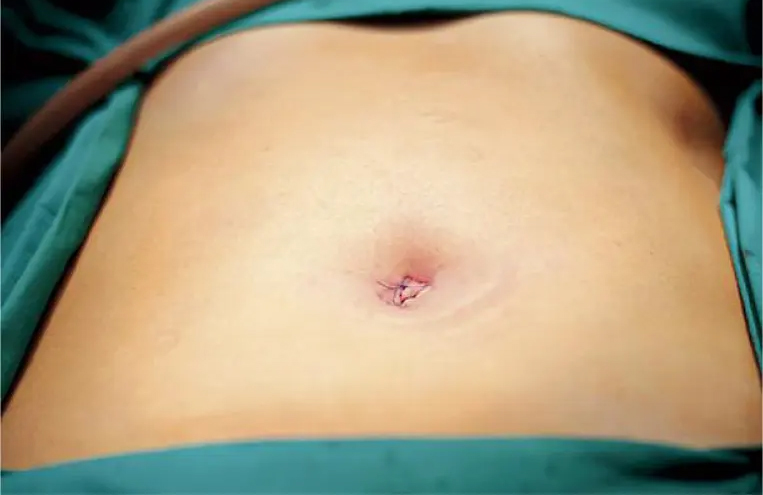
Single-Site Tubal Ligation is a state-of-the-art procedure for permanent birth control. It involves a single, small incision in the belly button, offering a highly effective solution with little to no cosmetic scarring.
Ideal for those seeking permanent birth control, this minimally invasive option offers little to no scarring, a discreet appearance, and a quick recovery with a fast return to daily activities.
The Procedure:
Performed under anesthesia, Single-Site Tubal Ligation is a quick procedure involving just one small incision through which the fallopian tubes are accessed, resected, and, finally, removed from the body. This effective approach provides permanent sterilization with minimal disruption to your body and lifestyle.
Recovery and Aftercare:
Recovery from Single-Site Tubal Ligation is typically swift. Most patients can resume normal activities within a few days, with complete healing occurring within a few weeks. Our team will provide comprehensive aftercare instructions and support throughout your recovery journey.
With over 400 robotic surgeries as the primary surgeon, Dr. Lucas brings unparalleled expertise to the operating table. His role as a Proctor for da Vinci Robotic Surgery with Intuitive and his American Board of OB/GYN certification highlight his expertise in this advanced surgical technique. Dr. Lucas also has a designation/diplomat in minimally invasive gynecology.
Surgeons like Dr. Lucas use robotic technology to improve precision, flexibility, and control during procedures. This approach provides a clearer view of the surgical area and allows him to perform complex, delicate procedures that may be more difficult with traditional methods.